
Triage: BIBM for tonic clonic seizure x10 minutes long. UNK history. Postictal on arrival. BS 144
History: A male in his mid 40’s is brought in by rescue ambulance for seizure from the side of a swimming pool. Patient was not a very good historian at first but was able to eventually provide history and states that he woke up with heartburn started on 5:30 in the morning took his antacids but not his other medications then had a brief swim just there and back with friends then was out of the pool before he collapsed and then had a witnessed tonic-clonic seizure. The witness described 1 arm flaccid the other arm above his head and the legs stiff. Medics got 3 blood pressures in the 110’s range. Patient does complain of headache but no neck pain does complain of pleuritic chest pain. He denies melena or known history of anemia. No other complaints. No history of seizures.
Vital signs: HR: 94, RR: 16, BP: 91/65, SpO2: 97%
Physical Exam:
°GENERAL: Very lethargic with very soft voice where I have to put my ear right next to his mouth and keep prompting him to talk
°HEAD: Normocephalic, atraumatic
°NEUROLOGIC: Normal speech. No focal weakness. Alert and oriented.
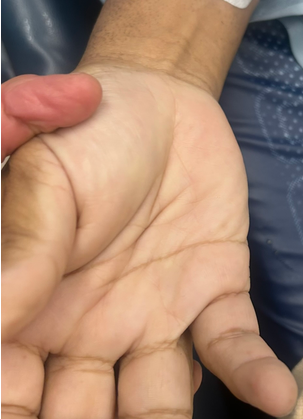
°SKIN: No erythema. Extremely pale palms African-American pigmentation. Pale palms could be due to severe anemia versus severe hypotension versus both
An ECG is done
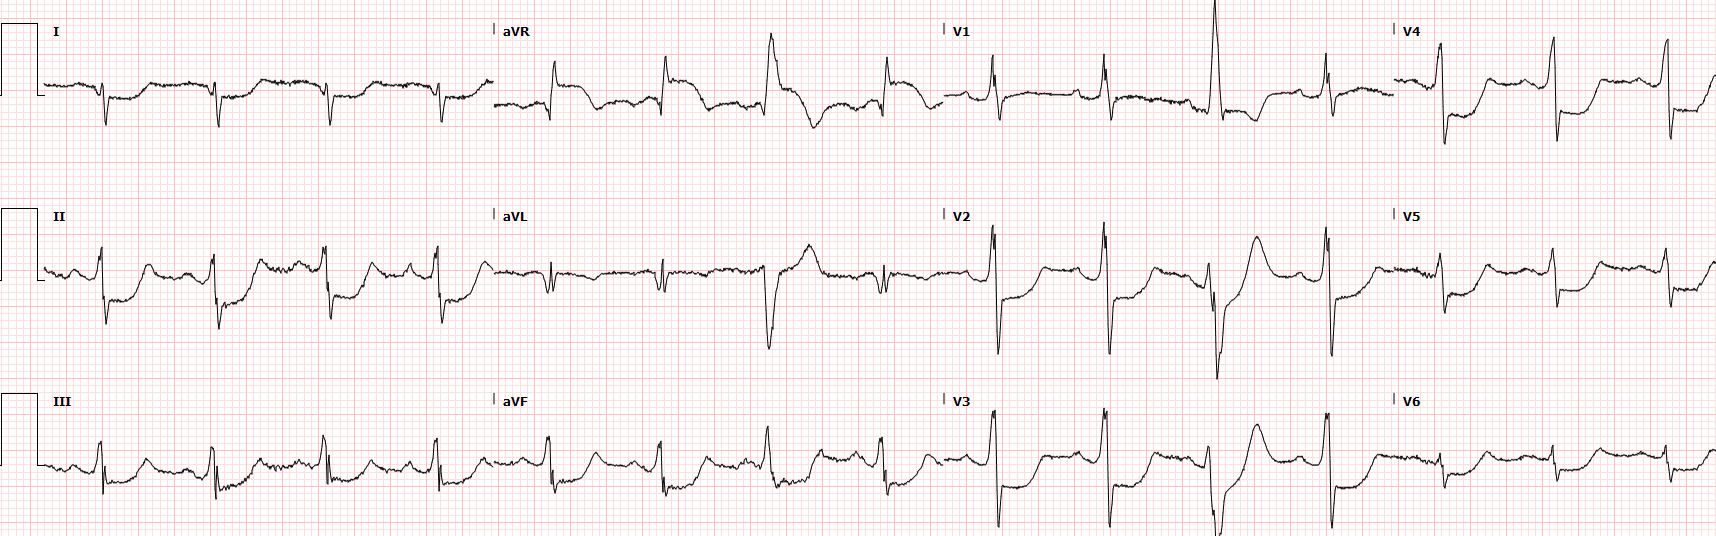
Computer Read: SINUS RHYTHM AT 96
RIGHT AXIS DEVIATION
RIGHT BUNDLE BRANCH BLOCK
MARKED ST DEPRESSION, CONSIDER SUBENDOCARDIAL INJURY
MDM: Code STEMI was called. Patient noted to be hypotensive and all arms without palpable pulses very lethargic. I ordered uncrossed match blood based on hypotension EKG changes and physical exam features suggestive of severe anemia. Hemoglobin level did come back at 9.4 but this could be early and an acute GI bleed as he does have normocytic indices so this still could be an acute GI bleed. Troponin slightly elevated repeat EKG unchanged. Blood transfusion ordered. Other labs ABG and official read of CT is pending but on CT of the chest abdomen pelvis there is no obvious intercranial or intra-abdominal bleed or dissection or pulmonary embolism. Cardiology is planning to take the patient to the Cath Lab. Was delayed to Cath Lab based on multiple other diagnostic considerations and testing. Clinical status has been improving slowly
What is the most likely cause of ECG findings in this patient?
- A) Acute coronary occlusion
- B) Blood clot (PE)
- C) Cardiac tamponade
- D) Drug toxicity
- E) Electrolyte issue
Bonus Question: Your resident wants to order albuterol for her COPD. Should you agree?
SCROLL DOWN FOR THE EKG ANALYSIS & 1-MINUTE CONSULT
<<<<<<<<<<<<<<<<<<<<< ADVERTISEMENT & SPACER >>>>>>>>>>>>>>>>>>>>>
THE EMERGENCY MEDICINE POCKETBOOK TRIFECTA

- Emergency Medicine 1-Minute Consult, 5th edition
- A-to-Z EM Pharmacopoeia & Antibiotic Guide, 5th edition
- 8-in-1 Emergency Department Quick Reference, 5th edition
******************************************************************************
<<<<<<<<<<<<<<<<<<<<<<<<< END SPACER >>>>>>>>>>>>>>>>>>>>>>>>>
ECG interpretation:
QUIZ ANSWER:
Case Outcome: