
Triage: BIBA from home c/o SOB x2 days. diarrhea, subj. fever at home, productive cough, body aches. Called 911 this AM after apple watch woke her up with a “critical alert”. History of asthma and anxiety. Used inhaler at home w/o relief. Lungs clear to auscultation
History of Present Illness: A woman in her early 40’s presents with 2 days of shortness of breath and 3 weeks of cough. She is also had fevers and diarrhea. She denies any vomiting with the diarrhea or abdominal pain. She tried her albuterol inhaler which did not help. Other than asthma and anxiety only other history is IVF years ago as her kids are currently 3 and 5.
Vital Signs: T: 37.2 °C, HR: 110, RR: 17, BP: 114/72, SpO2: 98%
Physical Exam: other than tachycardia her exam is normal without wheezing or rales
Initial Diagnostic Testing:
- EKG: see below.
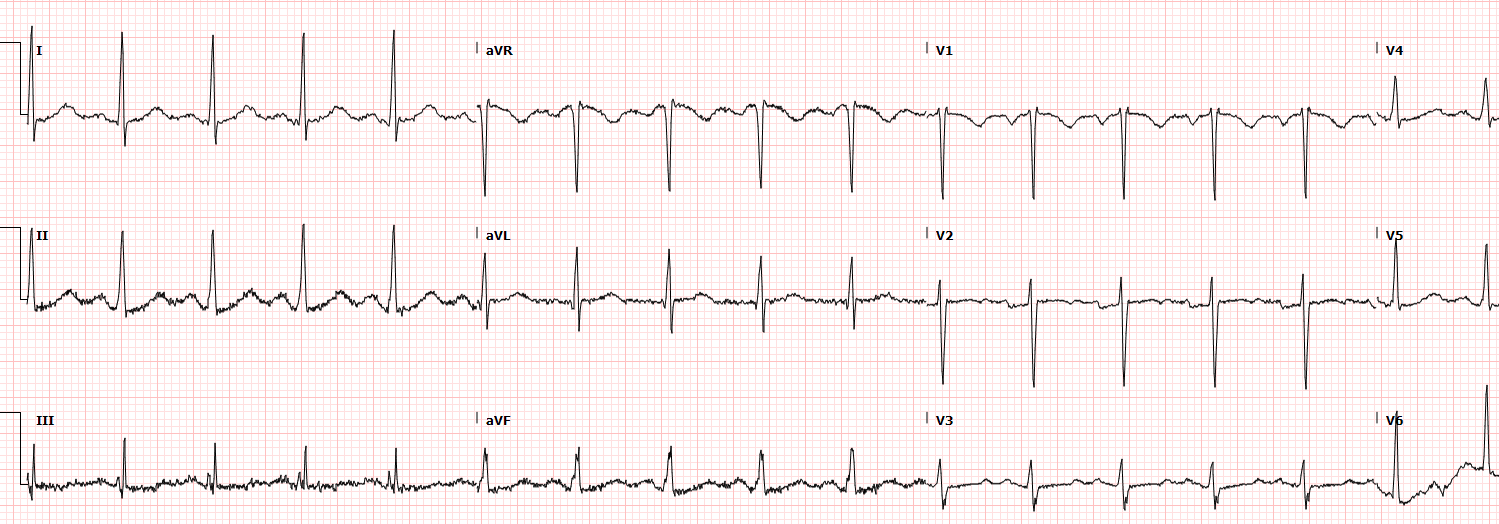
- Computer Read: Sinus tach at 119, possible LAE
- Chest x-ray: negative except for left basilar atelectasis
- CBC: normal
- Chemistries: normal with negative beta HCG
What is the best plan?
- A) IV fluids and admit for early pneumonia
- B) Ativan for anxiety and discharge for URI
- C) CT chest for dissection/PE
- D) None of the above
SCROLL DOWN FOR THE EKG ANALYSIS & 1-MINUTE CONSULT
<<<<<<<<<<<<<<<<<<<<< ADVERTISEMENT & SPACER >>>>>>>>>>>>>>>>>>>>>
THE EMERGENCY MEDICINE POCKETBOOK TRIFECTA

- Emergency Medicine 1-Minute Consult, 5th edition
- A-to-Z EM Pharmacopoeia & Antibiotic Guide, NEW 5th edition
- 8-in-1 Emergency Department Quick Reference, 5th edition
******************************************************************************
<<<<<<<<<<<<<<<<<<<<<<<<< END SPACER >>>>>>>>>>>>>>>>>>>>>>>>>
My ECG interpretation:
- Really just tachycardia that is actually higher than the HR in triage (normally the rate on the ECG is 15-20 bpm LESS than the pulse in triage
- Of note, her pulse did not slow down after 2L of IV fluids
- When there is tachycardia from PE there is usually also RAD or T inversion in the inferior and/or anterior leads, but not in this case.
ANSWERS:
- A) IV fluids and admit for early pneumonia – reasonable, but not the best plan
- B) Ativan for anxiety and discharge for URI – beware of diagnosing anxiety and ACS and PE symptoms can closely mimic anxiety
- C) CT chest for dissection/PE – reasonable
- D) None of the above – I gave IV fluids and pulse did not drop, which increases the chance of PE so D-dimer was sent and was massively elevated
1-Minute Consult on the topic for this case from the Emergency Medicine 1-minute Consult Pocketbook
CASE CONCLUSION: CXR negative, Covid positive, D-dimer 28 x ULN, CT chest with extensive bilateral PE’s. She hadn’t brought up any pain complaint and I hadn’t asked initially but she did have some left flank pain. It wasn’t bad but was worse with deep breathing.
CASE LESSONS:
- Beware of triage bias or your own bias for anxiety
- Investigate unexplained tachycardia that persists in the ED
- Young adults with PE often have no known risk factors
- Most common ECG finding in PE include the 4 T’s: Tachycardia, T inversion, flat T or Totally normal. The first 3 are usually from large PE’s.